Intake, classic form
New patient registration template
A new patient registration with Medicare and concession details, preferred clinician, medicines and allergies, record consent, reminders and emergency contacts.
19 questions, 16 required, as a classic form
Use this template opens a copy in the form builder after you sign in. Adapt it with AI opens the generator with this template chosen, so you can describe your business and get the questions rewritten for it.
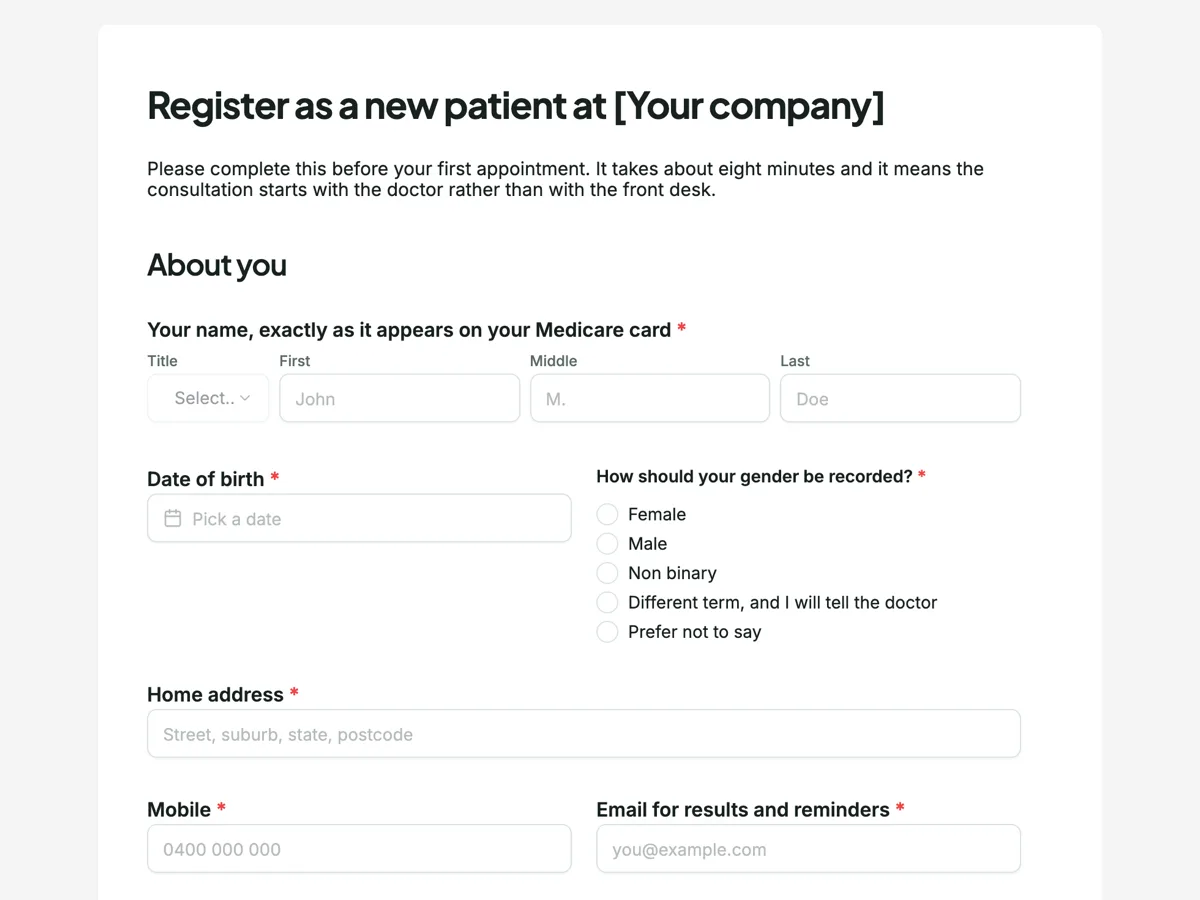
Every question
Your name, exactly as it appears on your Medicare card (required)
Full name
Date of birth (required)
Date
How should your gender be recorded? (required)
Single choice: Female, Male, Non binary, Different term, and I will tell the doctor, Prefer not to say
Home address (required)
Short answer
Mobile (required)
Short answer
Email for results and reminders (required)
Short answer
Medicare number (required)
Short answer
IRN, the number beside your name (required)
Short answer
Medicare card valid to (required)
Date
Concession or veterans card (required)
Single choice: None, Pensioner Concession Card, Health Care Card, Commonwealth Seniors Health Card, DVA Gold Card, DVA White Card
Private health fund and membership number, if you have one
Short answer
Preferred GP (required)
Dropdown: [Doctor 1], general practice and skin checks, [Doctor 2], chronic disease and diabetes, [Doctor 3], women and children, [Doctor 4], mental health and sports injuries, No preference, whoever is available soonest
Your previous practice, if you had one
Short answer
Medicines you take regularly (required)
Long answer
Allergies and reactions (required)
Long answer
May the practice upload to and view your My Health Record? (required)
Single choice: Yes, upload summaries and view my record, View only, do not upload anything, No, do not use My Health Record for me, I do not have one
Reminders and recalls by SMS
Multiple choice: Appointment reminders the day before, Recalls when a result needs discussing, Preventive reminders such as vaccinations and screening
Emergency contacts (required)
Table
Signature, or a parent or guardian if the patient is under 16 (required)
Signature
What you fill in
- [Your company]
- [Doctor 1]
- [Doctor 2]
- [Doctor 3]
- [Doctor 4]